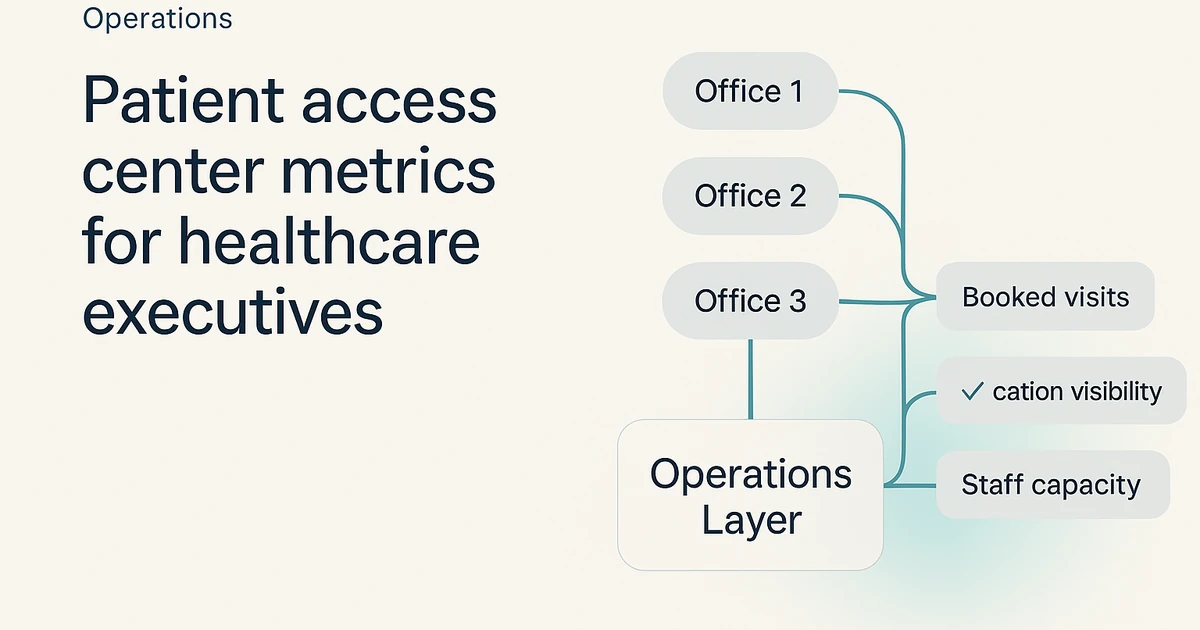
Front desk staffing has become a patient-access risk for multi-location healthcare groups, not just an HR problem. When a coordinator leaves, the immediate vacancy is visible. The harder damage often appears later: calls wait longer, schedules are handled differently from one site to another, managers spend their week filling coverage gaps, and new hires learn through local workarounds instead of a shared operating standard.
MGMA has continued to identify staffing pressure and turnover as material practice-management concerns. For a group with three or more locations, a 30% to 40% annual turnover pattern means leadership may be replacing roughly one-third of the front-office team every year. The result is a recurring reset of patient-access capacity just as the organization is trying to standardize it.
The useful executive question is not simply, “How can we hire faster?” It is, “Which patient-access work must remain at the site, and which work should have coverage, training, and measurement that do not disappear when one person resigns?” That question belongs inside the broader enterprise operating model, alongside growth, integration, and quality-control decisions.
Table of Contents
- Why does front desk turnover become an enterprise operations problem?
- What does turnover really cost beyond recruiting?
- Why is “hire better” necessary but insufficient?
- Which front desk work should stay local, and what can be centralized?
- How can leaders create coverage without overstaffing every location?
- What should an executive dashboard show during a staffing disruption?
- What is a sensible 90-day response to persistent turnover?
Why does front desk turnover become an enterprise operations problem?
At one location, a manager can often absorb a short vacancy. At fifteen locations, the same pattern creates a network problem. A call-out at one site can coincide with a queue spike at another; an experienced employee may be pulled away from patients to answer phones; a regional leader may discover a service failure only after a schedule looks thin or a complaint reaches the office.
The pressure multiplies because the front desk carries several jobs at once. Team members may greet arriving patients, answer calls, confirm appointments, manage intake paperwork, respond to messages, explain basic scheduling options, collect information for the next step, and coordinate with clinical staff. Those tasks do not peak evenly. Phone volume may rise when the waiting room is busiest, and a lunch break or a single absence can expose the lack of backup.
That is why groups should treat front-office turnover as a capacity-design issue. A staffing plan that works only when every site is fully staffed has no meaningful margin for PTO, parental leave, sick days, acquisitions, or normal attrition. A more resilient design separates work that requires local knowledge from work that can be handled through a shared process.
For a fuller view of that architecture, see the multi-location healthcare intake framework. It helps distinguish a local relationship task from a repeatable patient-access task, which is the distinction a staffing model must make before it can scale.
What does turnover really cost beyond recruiting?
The direct cost is easy to see: recruiting time, advertising, onboarding, temporary coverage, and the manager’s time. The less visible cost is operational variance. A new team member may need time to learn scheduling rules, provider preferences, insurance-related handoffs, escalation paths, and the practice-management system. During that ramp, calls may take longer and exceptions may be routed inconsistently.
For a multi-location group, the right unit of analysis is not only cost per departure. It is the cost of losing a reliable patient-access capability at one location while leaders try to maintain service levels across all locations. A vacancy can produce overtime, deferred administrative work, more manager intervention, or uneven call handling. None of those effects need to become permanent to affect capacity planning.
Executives should calculate the local cost using their own payroll and operating data rather than relying on a generic industry estimate. A useful review includes five questions:
- How many days pass between a departure and independent productivity for the replacement?
- Which duties are left uncovered, deferred, or transferred during that period?
- What happens to call answer rate, average speed to answer, and booking activity at the affected site?
- How much regional or location-manager time is diverted into interviewing, schedule coverage, and retraining?
- Does the group have a documented backup path when two people are absent at the same time?
This is also why workforce decisions should be read beside patient-access metrics. A dashboard that only reports headcount will miss whether staffing instability is becoming an access problem. The patient access center metrics guide explains the enterprise measures that can reveal variation before it becomes a recurring location issue.
Why is “hire better” necessary but insufficient?
Better recruiting is worthwhile. Clear job descriptions, realistic shift expectations, structured interviewing, a defined onboarding path, and competitive local compensation can reduce avoidable turnover. But recruiting does not remove the basic dependency created when one role owns every incoming call, every scheduling exception, and every piece of site-specific knowledge.
The same constraint applies to wage increases. Higher pay may improve a group’s position in a local labor market, but it does not create coverage during simultaneous absences or make training consistent across locations by itself. If the only response to turnover is another requisition, the organization keeps paying to restore the same fragile design.
This is especially clear during acquisition integration. A new location may bring its own phone habits, appointment types, staffing expectations, and informal scripts. Without a shared intake process, the acquired office becomes another distinct training environment. The group is then scaling differences rather than scaling an operating model.
The practical goal is not to eliminate local expertise. It is to document and route it. Returning-patient relationships, provider-specific exceptions, and high-touch issues may need local ownership. Routine appointment requests, basic service questions, confirmations, overflow calls, and after-hours intake should have a defined path that does not depend on the availability of one receptionist.
Which front desk work should stay local, and what can be centralized?
The answer varies by specialty and workflow, but the decision should be deliberate. Local staff often add the most value when a patient is physically present, when a clinical team needs immediate coordination, or when an issue depends on site context. Centralized or shared capacity is often better suited to repeatable work with clear scripts, system access, and escalation rules.
For example, a dental group may keep in-office treatment-plan coordination and chairside schedule changes close to the practice while centralizing new-patient calls and routine confirmations. An optometry group may preserve optical-floor coverage and provider-specific scheduling exceptions locally while moving overflow and recall-related phone work to a shared team. A veterinary group may need a clear clinical escalation protocol for urgent calls, but can still standardize appointment requests, general information, and after-hours routing.
Centralization is not an instruction to send every interaction to an anonymous queue. It is an operating choice with prerequisites: a current scheduling rule set, clear transfer standards, role-based system access, QA review, and a named owner for exceptions. MGMA’s guidance on centralized scheduling similarly frames centralization as a way to support growth when organizations design the process and governance around it, rather than merely reroute calls.
Groups evaluating a managed model can compare this work with the services described on MyBCAT’s patient-access solutions page. The key evaluation question is whether the model adds dependable capacity and visibility without losing the handoff quality that patients and location teams need.
How can leaders create coverage without overstaffing every location?
The usual failure mode is binary: staff each location for its highest predictable demand, or staff narrowly and accept voicemail and overload during peaks. Both approaches are expensive in different ways. The first duplicates capacity across every site. The second makes patient access contingent on a thin local roster.
A more practical approach is to build layers of coverage. Local teams own the in-person experience and clearly defined exceptions. A shared intake function handles common phone work and scheduled overflow. A documented after-hours route protects patients from dead ends outside normal hours. The group then uses reporting to decide when the mix needs adjustment rather than relying on anecdotes from the loudest location.
The management discipline matters as much as the staffing layer. Each queue should have a stated owner, an escalation path, and a definition of what counts as answered, transferred, abandoned, or resolved. Each location should know when it is expected to take a warm transfer and when a shared team can complete the task. Those details keep a centralized model from becoming a new source of confusion.
Quality assurance should also be calibrated across the network. A location manager and a centralized team can both believe they are following the process while using different language, different scheduling choices, or different rules for outbound follow-up. The multi-location call center QA calibration guide outlines why shared scoring and regular calibration are essential when more than one team touches the patient journey.
What should an executive dashboard show during a staffing disruption?
Do not wait for an annual turnover report. A useful operating dashboard lets leaders see whether a departure is affecting access this week and whether one location is absorbing more strain than another. The exact metric definitions should fit the group’s systems, but the dashboard needs enough detail to separate volume changes from service failures.
Start with inbound demand, answer rate, average speed to answer, abandonment, transfer rate, booking or next-step completion, and after-hours handling. Segment those measures by location, daypart, call type, and staffing condition when possible. Add a view of open roles, tenure, ramp status, PTO coverage, and repeated escalations. That combination gives operations leaders a way to ask a better question than “Are we short staffed?” They can ask where patient access is becoming unstable and what kind of capacity would correct it.
Do not use one network average as the only indicator. A strong result from several stable sites can hide a serious problem at a newly acquired office or a location with repeated turnover. Variance matters. Leaders need a consistent metric dictionary so that a call counted as answered or a booked appointment means the same thing across the group.
For organizations with formal governance requirements, this dashboard should connect to reporting, QA, and staffing decisions. The enterprise reporting and QA approach is a useful reference point for making the data review part of an operating cadence instead of a monthly slide.
What is a sensible 90-day response to persistent turnover?
The first 30 days should establish the baseline. Map inbound call paths, list every responsibility currently assigned to the front desk, identify peak periods, and quantify where coverage fails. Interview location leaders for exceptions, but validate the workflow in the phone and scheduling data rather than converting every preference into a permanent rule.
From days 31 to 60, standardize the highest-volume tasks. Write scripts and escalation rules, define who owns scheduling exceptions, create a shared training packet, and test overflow routing with a limited set of locations. Review real interactions for transfer quality and documentation accuracy. The aim is a workable shared service pattern, not a perfect process manual.
From days 61 to 90, expand only after the process holds. Compare performance between pilot sites and the baseline, calibrate QA with location leaders, and revise staffing assumptions based on actual demand. If the group works with an outside patient-access partner, use this period to confirm system access, privacy controls, escalation rules, and reporting responsibilities before broad rollout.
The durable output is not a hiring plan. It is a repeatable operating model: defined roles, documented exceptions, cross-site coverage, a training path, and a weekly review of patient-access performance. That model makes turnover easier to absorb because it reduces the amount of critical knowledge that exists only in one person’s head.
Key takeaways
Front desk turnover is expensive because it disrupts patient access, training consistency, and management capacity at the same time. Multi-location groups cannot solve that exposure through recruiting alone. They need to decide what work truly requires local ownership, build shared coverage for repeatable work, and measure whether staffing changes are affecting calls, scheduling, and handoffs.
For groups with three or more locations, the objective is not to remove the front desk. It is to stop treating every location’s front desk as an isolated staffing island. A standardized intake model, clear escalation rules, and calibrated reporting give operators more options when the labor market changes or another location is added.
Managing staffing pressure across 3+ locations? Request an Enterprise Assessment for your group.
Frequently Asked Questions
What is healthcare front desk turnover rate?
MGMA reports that staff turnover remains a significant medical-practice workforce issue. Individual front-desk turnover varies by market, specialty, schedule design, compensation, and management practices. A multi-location group should calculate its own annualized turnover by role and location so it can identify persistent hotspots.
How should a healthcare group respond when a front desk employee leaves?
Use the departure as an operating test. Confirm who covers calls, in-person check-in, scheduling exceptions, and follow-up work; monitor access metrics during the transition; and capture any undocumented process knowledge before it disappears. Repeated departures point to a workflow and coverage problem that should be addressed at the group level.
Does centralized intake replace local front desk staff?
Not necessarily. A centralized model can protect local teams from routine phone volume and provide overflow capacity while local staff focus on in-person service and exceptions that require site knowledge. The right division of work depends on the group’s specialty, systems, and patient journey.