Table of Contents
- Why Does Cloud Practice Management Change HIPAA Operations?
- What Should a Multi-Location Group Confirm Before Choosing a Cloud PMS?
- How Should Leaders Map ePHI Across the Practice Management Environment?
- Which Access Controls Matter for Centralized Teams?
- How Should the Buying Committee Evaluate Vendors and Support Partners?
- What Should Implementation Governance Look Like Across Locations?
- How Do You Keep Controls Working After Go-Live?
- FAQ
Cloud practice management is now the operating layer for scheduling, eligibility, reminders, billing handoffs, patient communications, reporting, and centralized support. For a healthcare group with three or more locations, the decision is not simply whether a platform has useful features. It is whether the platform and every workflow around it can support disciplined handling of electronic protected health information, or ePHI, as the group grows.
That is why HIPAA cloud practice management belongs on the operations agenda as well as the compliance agenda. The system touches front-desk teams, regional leaders, centralized schedulers, billing support, technology vendors, and sometimes an external patient-access partner. A configuration choice made during implementation can determine who sees records, who can export reports, and how quickly a group can investigate an access concern months later.
For an enterprise healthcare group, the practical goal is a defensible operating model: clear accountability, documented data flows, appropriate business associate relationships, role-based access, and repeatable review. A vendor cannot transfer that responsibility away. It can provide controls and evidence, but the group still has to decide how those controls are configured and used.
Why Does Cloud Practice Management Change HIPAA Operations?
A cloud practice management system may create, receive, maintain, or transmit ePHI in normal use. The compliance boundary therefore extends beyond the login page. It includes connected EHR workflows, patient messaging, billing handoffs, forms, document storage, call recordings, analytics, integrations, support portals, and backup or export processes.
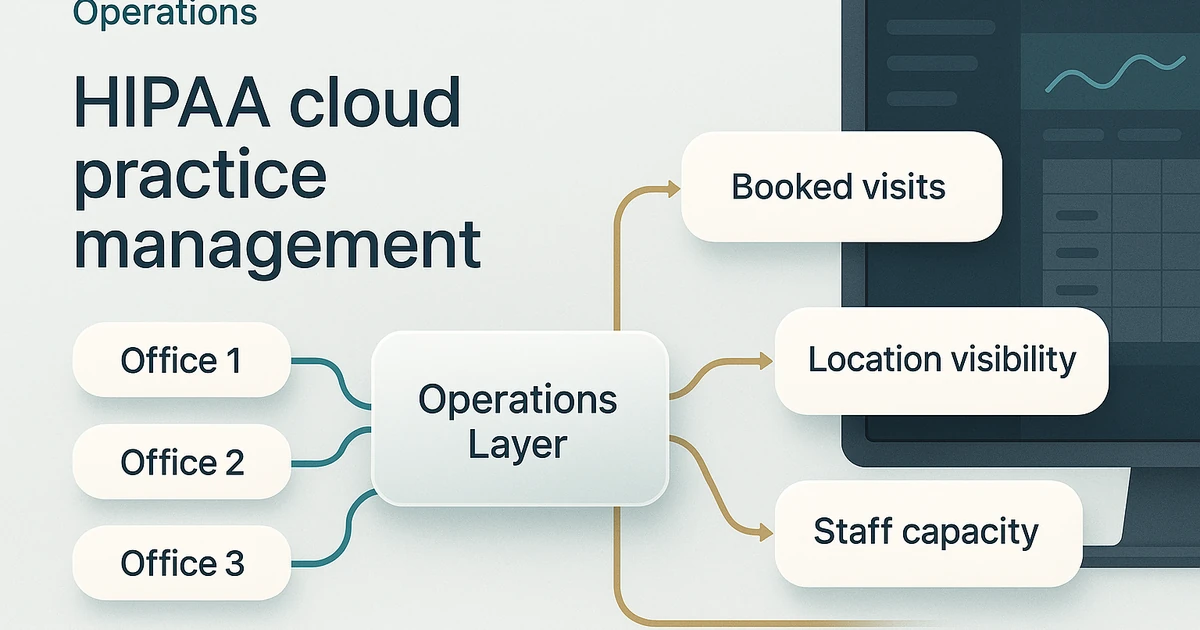
For one location, unclear permissions are already a problem. Across a group, they become harder to detect because centralization concentrates access. A scheduler covering several offices may need appointment and provider availability across those offices. A regional manager may need operational reporting without a broad view of patient-level records. A vendor support representative may need temporary access to resolve a configuration issue. Those are different use cases and should not be handled with one broad administrator role.
Centralized patient access can create more consistent processes when it is designed well. Our guide to enterprise centralized scheduling explains why a shared scheduling model needs defined ownership. From a HIPAA standpoint, that same ownership must extend to access, training, escalation, and audit review. Otherwise, the group may standardize the queue while leaving data handling inconsistent from location to location.
The right question is not, “Is this cloud PMS HIPAA compliant?” It is, “Can we configure this environment so each workforce member and vendor can perform an approved job without receiving unnecessary access?” That question produces a useful review of permissions, contracts, workflows, and evidence. A yes-or-no vendor claim does not.
What Should a Multi-Location Group Confirm Before Choosing a Cloud PMS?
Start with the system’s actual role in the group. A platform used only for appointment scheduling presents a different workflow from one that also holds clinical documentation, insurance details, payment-related information, patient messages, and call notes. The buying committee should document what information enters the platform, what leaves it, and which teams or vendors touch it.
The group should also confirm whether the contract structure matches that reality. When a vendor creates, receives, maintains, or transmits PHI on the group’s behalf, the legal and operational relationship needs review by the organization’s privacy, compliance, and legal stakeholders. This is not a contract-cleanup task for the end of procurement. It affects implementation sequencing, subcontractor review, incident procedures, and the support model.
Before selection, ask the vendor to demonstrate how the group will administer unique accounts, role-based permissions, location scopes, authentication, audit logs, export controls, and deprovisioning. A feature list is not enough. The team needs to see whether the platform can represent the group’s real structure: locations, centralized service teams, providers, regional leadership, temporary coverage, acquisitions, and approved outside support.
The HIPAA compliance overview is a useful companion when evaluating a patient-access provider. For broader operating-model questions, the enterprise healthcare operations page frames the same issue at group scale: standardize what should be repeatable, then make exceptions visible and controlled.
How Should Leaders Map ePHI Across the Practice Management Environment?
The most useful risk review begins with a data-flow map, not a generic questionnaire. Follow one ordinary workflow from first contact through scheduling, confirmation, service delivery, billing handoff, follow-up, and reporting. Record where ePHI is created, received, maintained, or transmitted at each point. Then repeat the exercise for less common but high-risk paths, such as a rescheduled appointment, a system outage, a vendor support request, an export for a manager, or a location transition.
The map should include the core PMS and EHR, but it should not stop there. Patient communication tools, integrated forms, reminder vendors, call-center software, document repositories, analytics tools, support ticketing systems, and backup processes may all be relevant. Manual work deserves the same scrutiny. A spreadsheet download, emailed attachment, screenshot, shared inbox, or copied call note can change the risk profile even when the core platform is configured carefully.
For multi-location groups, cross-location activity needs its own column in the map. Identify which roles work across locations, whether access is persistent or temporary, and how the organization confirms business need. A manager who needs aggregate scheduling performance may not need patient-level detail. A centralized scheduler covering an office for a shift may need a time-limited location scope rather than permanent group-wide access.
This exercise also improves technology decisions. When evaluating EHR and PMS integration for centralized scheduling, a group can compare the intended workflow against the actual systems and fields involved. That gives operations, IT, and compliance a shared record of what must be controlled before rollout.
Which Access Controls Matter for Centralized Teams?
Least privilege is an operational design choice. It means assigning access based on the minimum information and capability needed for an approved job, then reviewing that assignment when the job changes. It does not mean making centralized work impossible. It means translating responsibilities into roles that can be configured and audited.
Define standard roles before implementation: front desk, scheduler, billing support, location manager, regional operator, provider, system administrator, and vendor support. For each role, specify the business purpose, applications, location scope, functions available, approval owner, and removal trigger. The details will differ by organization, but the decision record should be consistent.
Unique user accounts are essential to accountability. Shared credentials make it difficult to confirm who accessed a record, changed an appointment, or exported a report. Groups should also establish a controlled process for temporary coverage. The request should identify the user, location, purpose, approver, start date, and expiration date. Access that expires automatically is easier to govern than access granted during an urgent staffing moment and forgotten afterward.
Audit logs should support a defined review process rather than sit unused. Decide which events merit routine review, who owns exceptions, and how the group documents corrective action. Useful examples may include administrative changes, unexpected exports, failed authentication patterns, or access that does not match a user’s role. The goal is not to create a surveillance project. It is to make material access events reviewable when they matter.
For a centralized intake operation, access design must stay aligned with the service model. The comparison in centralized versus distributed intake can help leadership define where work belongs. The HIPAA control question is then straightforward: which roles require which location scope to carry out that model?
How Should the Buying Committee Evaluate Vendors and Support Partners?
Vendor due diligence should connect product claims to the group’s own data-flow map. Ask a cloud PMS vendor how it handles user administration, auditability, support access, data availability, backups, maintenance notices, incident communication, subcontractors, and configuration changes. Ask the same questions of connected vendors and patient-access partners when their work touches PHI.
The answers should become documented operating requirements. For example, a group may require individual accounts for support personnel, named approval for elevated access, a defined method to remove access at separation, a record of subcontractors with relevant access, and an escalation path for an incident or service interruption. Those requirements can be validated during procurement, implementation, and ongoing governance.
Support access is often overlooked. A vendor may need to troubleshoot an integration, a permission issue, an appointment template, or a reporting discrepancy. That does not justify informal, open-ended access. The group should know how support access is requested, approved, scoped, logged, and removed. The same standard applies to internal teams and outsourced teams.
When the decision includes patient-access outsourcing, use a structured evaluation rather than a sales-demo impression. Our patient-access compliance guide discusses the relationship between operational controls and vendor assessment. The decision should also clarify who owns frontline workflow design, quality review, escalation, and access administration after launch.
What Should Implementation Governance Look Like Across Locations?
Implementation is the moment to replace inherited permissions with a defined model. Before user provisioning begins, establish the approved role matrix, location rules, administrator model, support-access process, audit expectations, and downtime procedure. Then test those controls with representative users from locations, centralized teams, and management rather than assuming that a system configuration works because it looks correct in a project meeting.
Training should focus on the workflows people will actually perform. Policy training remains important, but a scheduler also needs to know how to use the approved account, when a cross-location record is appropriate to open, how to document only what is necessary, where to route an exception, and what to do when a system is unavailable. Supervisors need to understand their role in quality review and escalation without routinely pulling patient details into broad reports.
A phased rollout is often easier to govern than a group-wide switch. Use the first locations to validate role assignments, integration behavior, service queues, reporting, and downtime steps. Capture the decisions that change during the pilot, then update the standard rollout packet before expanding. This is especially important after acquisition activity, when legacy location practices may differ from the target operating model.
The group should keep implementation artifacts together: the role matrix, data-flow map, relevant vendor documentation, approved workflows, training materials, pilot findings, exception decisions, and ownership list. These materials reduce dependence on individual memory when a new location, manager, or vendor enters the environment.
How Do You Keep Controls Working After Go-Live?
The cleanest implementation will drift without recurring review. Employees change roles, locations open or close, new integrations are added, managers request reports, and vendors change their products or support arrangements. Each change can alter who has access to ePHI and how it moves through the organization.
Set a recurring cadence that fits the group’s risk profile and operating rhythm. Review active accounts and location scopes, confirm that departed or reassigned users no longer have unnecessary access, examine administrator assignments, and verify that key vendors still match the group’s documented workflows. Include patient-access operations in that cadence. A call-handling or scheduling process can change without a formal software project, yet still affect the data flow.
Change management should trigger a focused review before new functionality reaches production. The intake can be simple: what is changing, which systems and roles are affected, what information is involved, whether a vendor relationship requires review, what training is needed, and who will verify the outcome. The value comes from making ownership explicit before a workaround becomes normal practice.
Finally, plan for interruptions. If the PMS or a connected tool is unavailable, staff will still need a way to serve patients and coordinate operations. The downtime procedure should identify approved communication channels, who can authorize exceptions, where temporary information is handled, and how records are reconciled afterward. An unplanned workaround is rarely as controlled as a rehearsed one.
FAQ
Is a cloud practice management vendor responsible for the group’s HIPAA compliance?
The vendor may have obligations based on its role and contract, but the healthcare group still needs to manage its own compliance responsibilities. The group must assess its workflows, configure access appropriately, oversee relevant vendor relationships, and respond when its operating model changes. Legal and compliance stakeholders should review the specific relationship and data flow.
Does centralized scheduling require every scheduler to have access to every location?
Not necessarily. Access should follow the coverage model and business need. Some groups may use defined regional teams, while others may use temporary cross-location coverage. In either case, the scope should be intentional, approved, and reviewable rather than granted broadly for convenience.
What should a group ask before giving a support partner PMS access?
Confirm the work the partner will perform, the systems and location scopes required, the account and authentication method, the approval owner, training expectations, quality oversight, how access is logged, and how it will be removed. If PHI is involved, bring the relevant privacy, compliance, and legal review into the decision early.
How often should access and vendor controls be reviewed?
There is no substitute for the organization’s own risk-based policy. At a minimum, review controls when a role changes, a location joins or leaves the group, a material integration is added, a vendor’s service changes, or an incident reveals a gap. A recurring documented cadence helps catch ordinary drift between those events.
Related Reading
- SOC2 Medical Answering Service Enterprise Healthcare
- Legal and Regulatory Compliance Strategies in Optometry
- BPO Security and HIPAA Compliance for Eye Care Practices
Sources
- ONC: Privacy, Security, and HIPAA
- ONC: Security Risk Assessment Tool
- HHS OCR: Breach Portal
- HHS OIG: General Compliance Program Guidance
Ready to Improve Your Patient Retention?
MyBCAT helps healthcare practices recapture missed calls and automate patient scheduling so no opportunity slips through the cracks.